


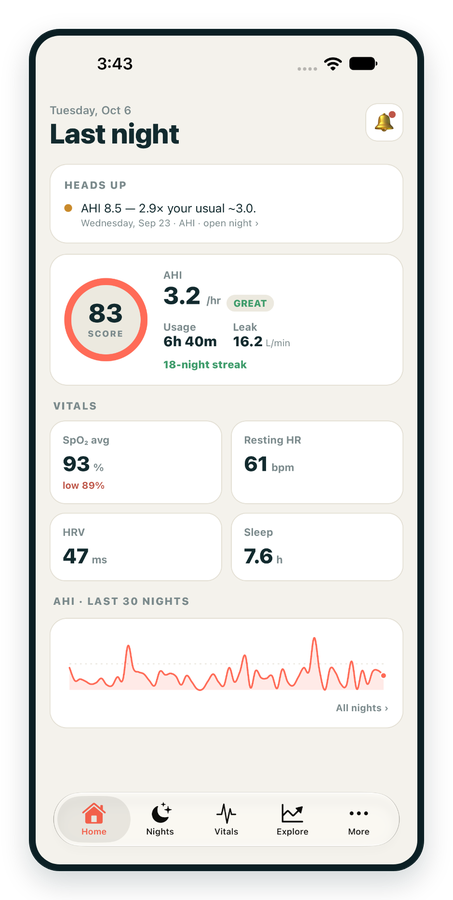
iPhone / iPhone Duo Live
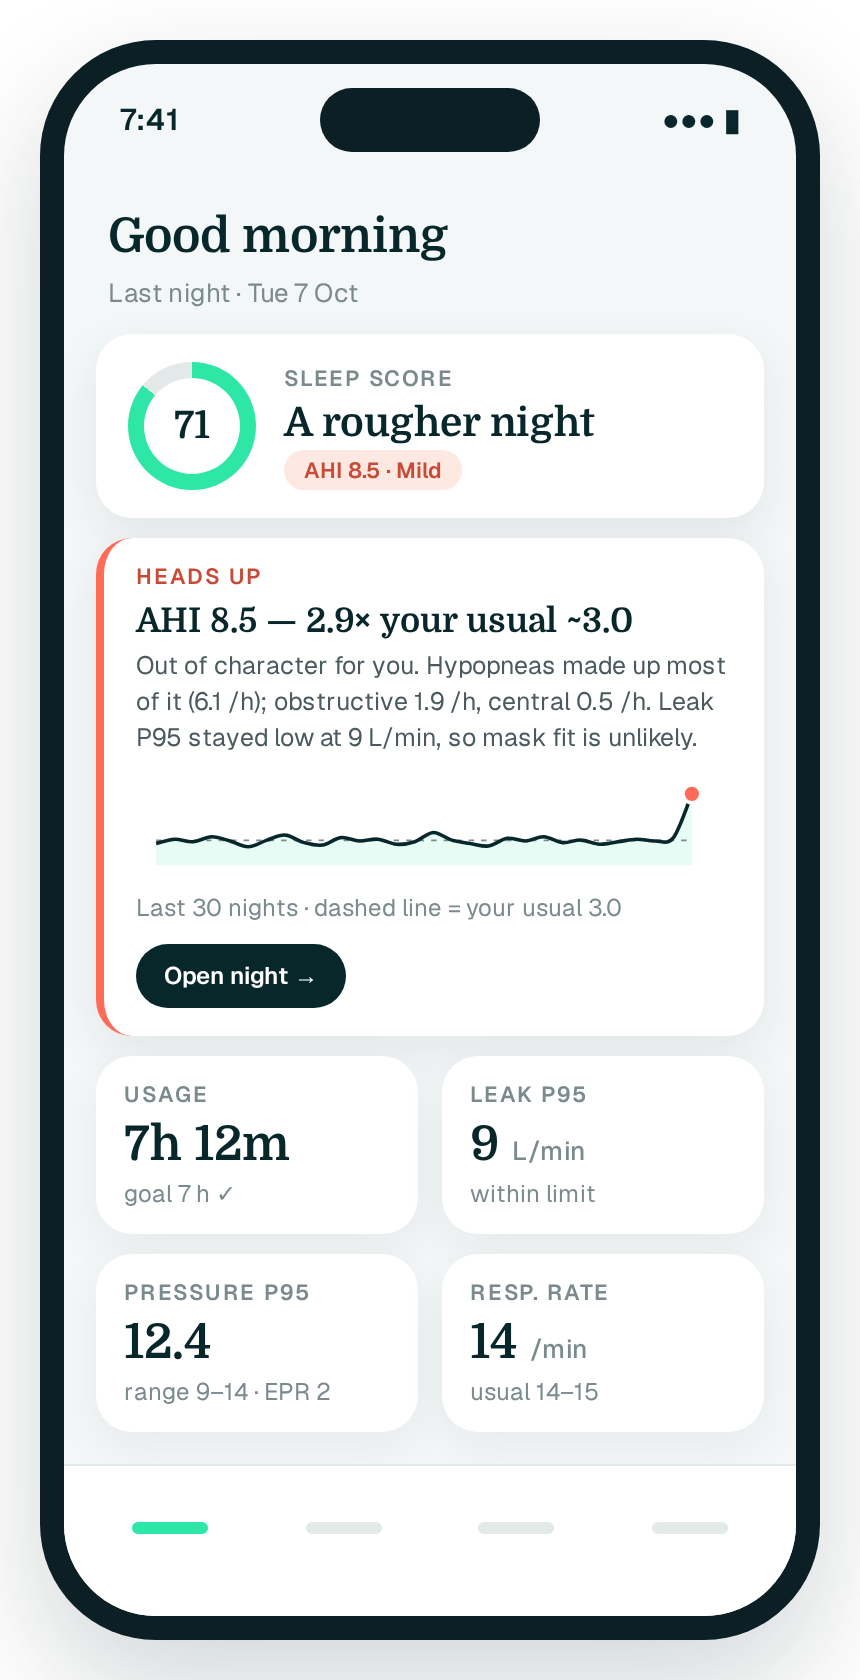
Last night before you are out of bed. Apple Health vitals, Face ID.
Download on the App Store Apnealytics
Free on every plan: unlimited imports, the full dashboard and your last 30 nights.
 Compatibility checkerWill my machine work?Type your model. You get a straight answer: supported, partial, waitlist, or why not.Check my machine
If it writes an SD card, we probably read it. ResMed AirMini has no card, so no app can read it.
Sleep Check-up
3 of 6 checks done
Six short screeners, one picture of how you sleep. Earn a milestone for each, save results and get retake reminders.
Latest milestone: Sleepiness check done
 NEWTrack your 90-day compliance windowOpen the calculator
13 free tools. No account needed — sign in to save results and fill answers from your own CPAP data.
Last night before you are out of bed. Apple Health vitals, Face ID.
Download on the App Store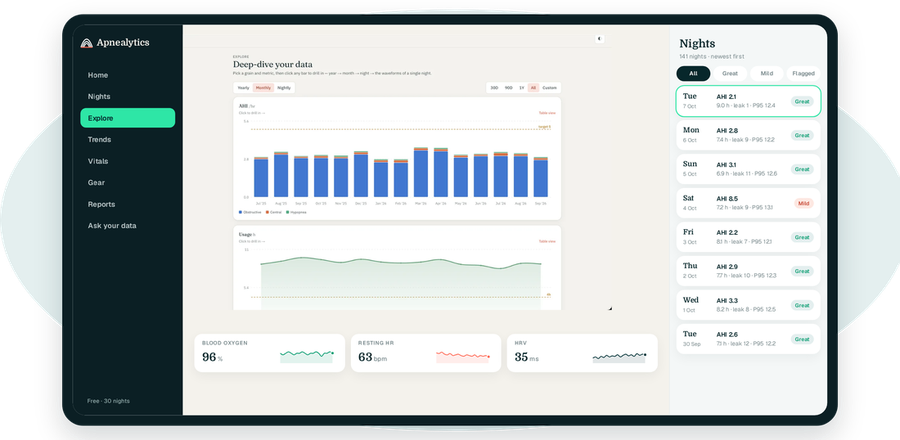
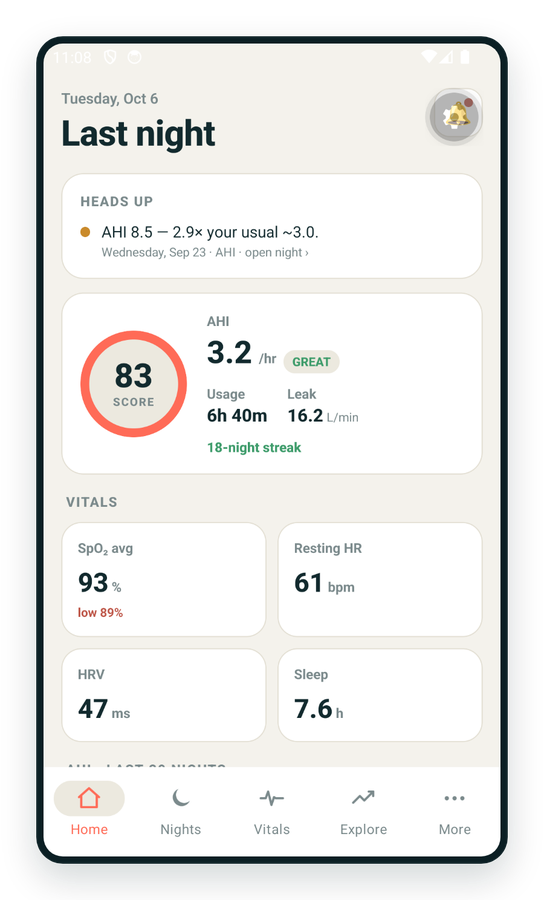
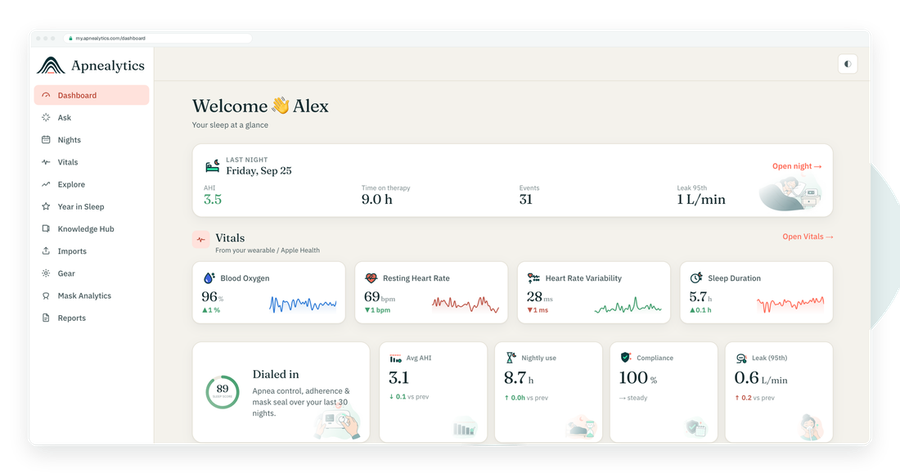
One account on every screen. Apple Watch vitals sync through Apple Health.
Open a night of CPAP data and you can be shown forty things. Six matter for almost every decision you or your clinician will make, and they are best read in a fixed order, because each tells you whether the next is trustworthy. This guide to how to read CPAP data goes through those six: usage hours, AHI, leak, pressure, event composition and oxygen. A low AHI on a two-hour night means little; a high AHI on a heavy-leak night may be a mask problem, not an airway problem. So you read usage before AHI, and leak before you trust AHI.
What it is: how long you wore the mask with the machine running.
What to look for: 4 hours is the US compliance threshold (4 or more hours on 70 percent of nights over a 30-day window within the first 90 days). More is better. Most people sleep 6 to 8 hours; usage should be most of that.
Why it comes first: every other number is averaged over this time. A 90-minute night can show a wonderful AHI and tell you nothing. Before you read anything else, check that there was enough night to read.
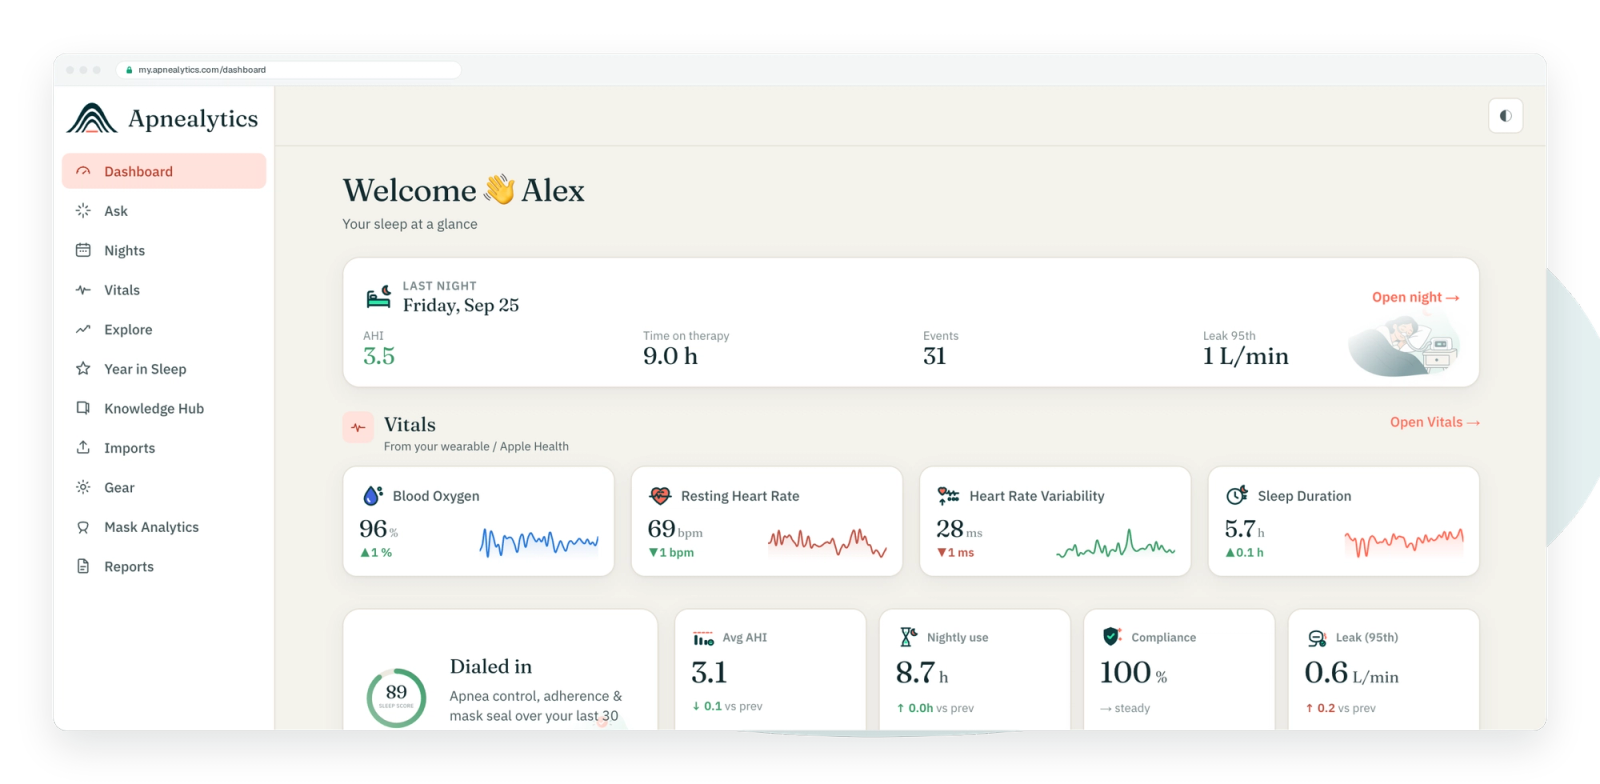
In Apnealytics: usage hours sit at the top of the nightly card, and the Goals and streaks panel tracks the 4-hour line. A "Heads up" alert fires when usage slips.
What it is: the Apnea–Hypopnea Index, the number of apneas and hypopneas per hour of use, as estimated by the machine from its flow sensor. It is an estimate, not a sleep study.
What to look for: under 5 is the conventional target on therapy. Apnealytics bands it: Great, Mild, Moderate, High. A single bad night is noise; three in a row is a pattern.
What not to do: react to one number. Look at the 30-night rolling trend before deciding anything changed.
In Apnealytics: last-night AHI with its band is the centre of the dashboard. The 30-night rolling AHI trend sits under it, and "What changed?" marks any point where the trend shifted or a setting changed.
What it is: air escaping the mask beyond the intentional vent flow. Reported as a rate in L/min. The useful summary is the 95th percentile, leak P95: the level that leak stayed under for 95 percent of the night.
What to look for: ResMed's large-leak threshold is 24 L/min. A P95 under that means the mask held nearly all night. Above it, the mask leaked heavily for at least 5 percent of the night, and during those stretches event detection and pressure delivery are both less reliable.
Why it comes before pressure and events: if leak was high, a high AHI may be the leak, not your airway. Fix the seal first.
In Apnealytics: leak P95 is on the nightly card. Mask Analytics shows seal, AHI and usage per mask.
What it is: on an auto-adjusting machine (AutoSet, VAuto), the pressure moves between the minimum and maximum your clinician set. Pressure P95 is the level it stayed under for 95 percent of the night. The median tells you where it spent most of its time.
What to look for: compare P95 with your set maximum. If P95 sits at the maximum night after night, the machine may want to go higher than it is allowed; that is a conversation for your clinician. If P95 sits well below the maximum with a fine AHI, the range is comfortable. Also note EPR (expiratory pressure relief), which drops pressure as you breathe out.
In Apnealytics: pressure P95 is shown against your set range, with EPR beside it. "What changed?" flags any night the settings were altered.
What it is: the AHI broken into obstructive apneas, central apneas, hypopneas and unclassified events.
What to look for: on CPAP, residual events are usually hypopneas and a few obstructives. A rising share of central apneas is worth noting: pressure does not treat centrals, and your clinician will want to know. The machine's labelling is an estimate from flow, so treat the split as a signal, not a verdict.
In Apnealytics: the event composition bar sits beside the AHI, and the per-night event strips on Pro show where each type clustered. The trigger journal lets you note alcohol, a cold or a new pillow and see whether AHI moved with it.
What it is: SpO₂ from an oximeter worn overnight, overlaid on the therapy timeline. The summary numbers are ODI₃ and ODI₄ (desaturations of 3 or 4 points per hour) and T90 (minutes below 90 percent).
What to look for: low ODI and a T90 near zero mean the remaining events are not costing you oxygen. A high T90 with a low AHI is a mismatch worth raising with your clinician.
Why it comes last: it is the outcome. The first five describe what the machine did; this one describes what your body did.
In Apnealytics: oximetry overlays are Pro, from the Wellue O2Ring, Contec CMS50 family, ResMed SAD.edf or any EDF/CSV oximeter. Apple Health / Health Connect SpO₂ averages (free) appear in the Vitals tiles.
Usage 7.2 h. AHI 2.1, Great. Leak P95 11 L/min. Pressure P95 10.4 against a 6–14 range, EPR 2. Events: 9 hypopneas, 4 obstructive, 2 central. ODI₃ 1.8, T90 0 min. Reading in order: enough night to judge, AHI low, leak low so the AHI is trustworthy, pressure in range, events unremarkable, oxygen held. Nothing to act on.
Now the same night with leak P95 at 38 L/min and AHI 7.4. Enough night, AHI Moderate, but leak was heavy, so the AHI may be a seal problem. Check Mask Analytics before worrying about the airway.
One odd night: note it in the trigger journal and move on.
Three nights the same way: check "What changed?" and leak, then wait a week.
A trend over 30 nights: bring the chart to your clinician. The doctor-ready PDF on Pro puts the six numbers on one page.
Under 5 events per hour is the conventional target on therapy, and many people run between 1 and 3. Read it alongside usage and leak: a low AHI on a short or leaky night is less meaningful. A single night above 5 is noise; a 30-night trend above 5 is worth a conversation with your clinician.
ResMed treats 24 L/min as the large-leak threshold. A leak P95 under that means the seal held for at least 95 percent of the night. Occasional spikes are normal, especially when you turn over. A P95 consistently above the threshold suggests the mask size, type or strap tension needs attention.
It is the pressure your auto-adjusting machine stayed at or below for 95 percent of the night. If it sits at your set maximum most nights, the machine may be capped. If it sits well below the maximum with a good AHI, the range is working. Changes to the range are a clinician decision.
Check leak first. Heavy leak makes event detection and pressure delivery less reliable, so a high AHI on a high-leak night may be a seal problem. If leak is fine, look at event composition: a rise in central events is not treated by pressure and should be discussed with your clinician.
No. The first five numbers come from the machine's SD card. An oximeter adds the outcome: whether residual events are costing you oxygen. It is most useful when AHI looks fine but you still feel unrested, or when central events are rising. Apnealytics overlays oximetry on Pro.
The web app is live today. iPhone and iPad are on the App Store. Android is on Google Play. Your first 30 nights are free, forever.

 DashboardSleep Score, AHI band, leak and pressure
 Trends & historyA year down to a night
 Breath-by-breath viewerAirflow, pressure, leak tracesPro
 SpO₂ overlayOximeter data on the same nightPro
 Pressure insightsP95, set range, EPR and ramp
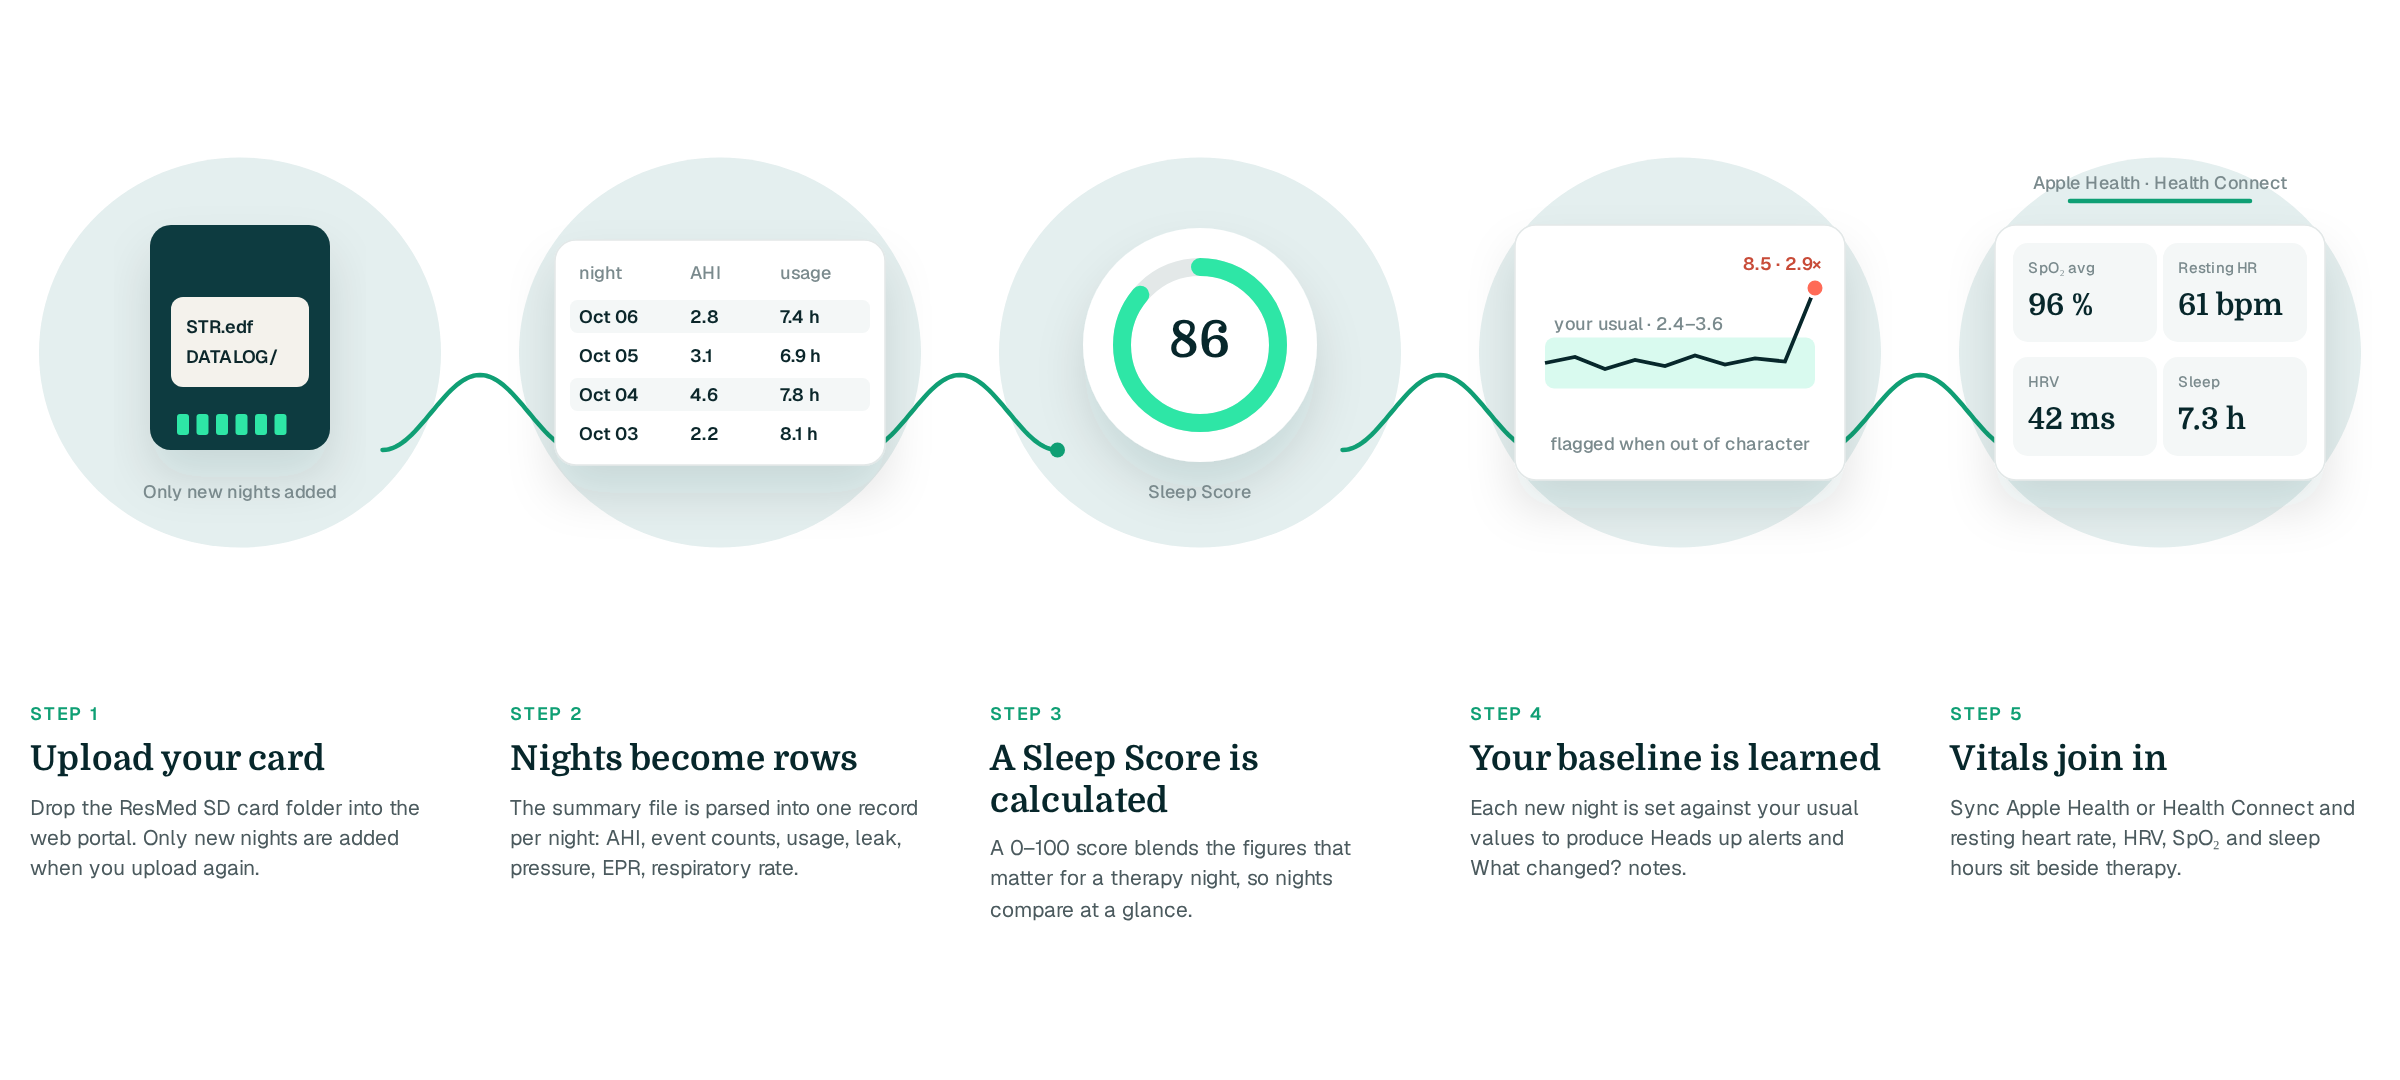
 SD card importDrop the card folder, only new nights added
 Mask fit & gearWhich mask actually seals
 Ask your dataPlain-English questions, your own AI keyBYOK
 Year in SleepYour therapy year in one storyNew
 Compliance reportFinds the qualifying window for youPro
 Share with your doctorRead-only, revocable links
 Companion appiPhone, iPad and Android
 Privacy & securityYour data, locked to you
 ResMed AirSense 10 & 11Supported
 ResMed AirCurve 10 & 11 VAutoSupported
 ResMed S9 / LumisSupported
 Philips DreamStation 1 & 2Supported
 Fisher & Paykel SleepStyleSupported
 Löwenstein / DeVilbissPartial
 React Health Luna G3Waitlist
 Transcend MicroWaitlist
 Full face masksFit, leak signature, Mask Analytics
 Nasal masksOver-nose and cradle styles
 Nasal pillowsMinimal-contact fit tips
 Wellue O2RingSupported
 Contec CMS50 familySupported
 Apple Health / Health ConnectResting HR, HRV, SpO₂, sleepSupported
 What is AHI?The apnea-hypopnea index, explained
 What is a good AHI on CPAP?
 CPAP leak rate explained
 Pressure settings explained
 Reading CPAP waveformsAll 14 explainers
 Apnealytics vs SleepHQ
 Apnealytics vs OSCAR
 Apnealytics vs myAir
 Apnealytics vs DreamMapper
 SleepHQ vs OSCARBest CPAP apps in 2026
 How to read CPAP dataStart here: six numbers, in order
 Read your CPAP SD card
 Share data with your doctorChoosing a CPAP mask
 Travel with CPAPAll guides
 Mask finderSeven questions, a ranked mask typeYour data
 Machine finderA two-machine shortlist for your prescription
 iPhone / iPhone DuoLast night before you are out of bed. Apple Health vitals, Face ID.Live
 iPadSame universal app, side-by-side panes and full-width waveforms.Live
 AndroidPhones, tablets and foldables, with Health Connect built in.Live
 Web portalWhere your SD card goes. Every chart, report and setting.Live


